
Diseases of the External Nose: Notes, Clinical Features, Treatment & MCQs
Introduction
Diseases of the external nose include congenital lesions, nasal deformities, infections, inflammatory disorders, benign tumours and malignant skin cancers. Important conditions include nasal dermoid, encephalocele, nasal glial heterotopia, saddle nose, nasal vestibulitis, furunculosis, perichondritis, rhinophyma, basal cell carcinoma, squamous cell carcinoma and melanoma.
For MBBS, ENT PG, NEET PG, INI-CET and FMGE, the most important approach is to recognise the clinical pattern and connect it with the likely diagnosis. A midline congenital nasal mass may represent a dermoid, encephalocele or glial heterotopia; hair emerging from a sinus strongly suggests a dermoid, whereas enlargement with crying or Valsalva suggests an encephalocele.
This chapter covers the classification, clinical features, diagnosis and treatment of external nose diseases, followed by a differential-diagnosis guide, high-yield revision points, mnemonics, FAQs and NEET PG-style MCQs.
Applied Anatomy of the External Nose
The external nose consists of a bony framework, cartilaginous framework, skin and soft tissue, blood supply, and nerve supply:
- Bony framework: Nasal bones and frontal processes of the maxilla.
- Cartilaginous framework: Upper lateral cartilages, lower lateral (alar) cartilages and septal cartilage.
- Skin and soft tissue: The skin is thin over the dorsum and thicker over the tip and alae.
- Blood supply: The external nose receives branches mainly from the ophthalmic and facial arteries, with extensive arterial anastomoses. The valveless venous connections of this region communicate with the cavernous sinus and have clinical importance.
- Nerve supply: Sensory supply comes mainly from the ophthalmic (V1) and maxillary (V2) divisions of the trigeminal nerve. The facial nerve supplies the muscles of facial expression and nasal musculature.
Classification of Diseases of the External Nose
For clinical and academic purposes, diseases can be systematically classified as:
| Category | Examples |
| I. Congenital Causes | Nasal dermoids, encephaloceles, gliomas, cleft nose |
| II. Nasal Deformities | Saddle nose, hump nose, crooked nose, tip deformities |
| III. Infective and Inflammatory Diseases | Vestibulitis, furunculosis, cellulitis, perichondritis |
| IV. Benign Conditions and Tumours | Rhinophyma, infantile hemangioma, epidermoid cyst, papilloma, papilloma, pigmented nevi |
| V. Malignant Neoplasms | Basal cell carcinoma, squamous cell carcinoma, melanoma, merkel cell carcinoma |
| VI. Systemic Diseases with Nasal Manifestations | Granulomatosis with polyangiitis, sarcoidosis, relapsing polychondritis |
Congenital midline nasal lesions
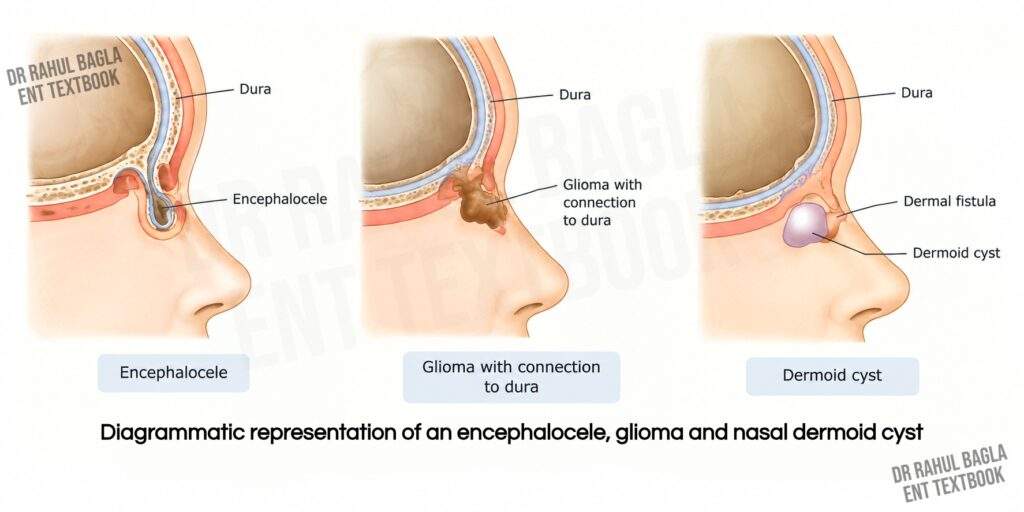
Congenital midline nasal lesions include dermoids, encephaloceles and nasal gliomas. These lesions may look similar clinically but differ in their intracranial connections and management. Do not biopsy or blindly excise a congenital midline nasal mass until imaging has excluded intracranial communication. An unrecognised intracranial tract can cause CSF leak, meningitis or intracranial injury.
1. Nasal Dermoid Cysts and Sinuses
Nasal dermoids are rare congenital midline lesions that contain ectodermal and mesodermal elements. They develop along embryonic fusion lines and represent the most common congenital midline nasal lesions. Nasal dermoids are rare, with reported incidence estimates of approximately 1 in 20,000–40,000 live births and show a male predominance of approximately 3:1.
Aetiology and Embryology: Nasal dermoids develop when ectodermal tissue becomes trapped during embryonic development. Incomplete closure of the fonticulus frontalis may trap dermal tissue between the developing nasal bones and cartilage. Persistent tissue in the prenasal space may also form a cyst or sinus. A tract may extend intracranially through the foramen caecum and attach to the dura.
Pathological Features: The lesion has a stratified squamous epithelial lining and may contain sebaceous glands, hair follicles, sweat glands, keratin and epithelial debris.
Clinical Features: Most lesions present at birth or during early childhood as a midline nasal swelling, usually between the columella and glabella. They may present as a cyst, sinus or fistula. Hair protruding from a sinus opening strongly suggests a dermoid. The swelling is usually firm and non-compressible and may discharge sebaceous material. Recurrent infection may occur. Rare complications include bony erosion, periorbital spread, meningitis and brain abscess.
Investigations: Use imaging to assess the lesion before surgery. MRI best demonstrates soft-tissue extent, sinus tracts, dural attachment and intracranial extension. CT provides better assessment of the bony anatomy and may show a bifid crista galli, widened foramen caecum or cribriform plate defect.
Anatomical Classification for Nasal Dermoids
| Type | Description | Surgical approach |
| Type I – Superficial | Limited to nasal soft tissue | Direct external excision |
| Type II – Intraosseous | Extends into nasal or frontal bones | Bony exposure or drill-out |
| Type III – Intracranial extradural | Extends intracranially without dural attachment | Frontonasal or cranial approach |
| Type IV – Intracranial intradural | Intracranial extension with dural attachment | Cranial or combined endoscopic-cranial approach |
Management: Perform complete surgical excision, which is usually curative. Choose the approach according to the depth and intracranial extension. Use external rhinoplasty, direct excision or selected endoscopic approaches for superficial lesions. Intraosseous lesions may require osteotomy or careful drilling. Intracranial extension often requires a combined ENT–neurosurgical approach with skull-base repair when necessary.
Postoperative Care: Monitor for CSF leak, infection and wound complications. Use antibiotics when clinically indicated and nasal packing when required. Long-term follow-up, including MRI when appropriate, can help detect recurrence.
2. Nasal Encephalocele / Meningoencephalocele
A nasal encephalocele occurs when intracranial contents herniate through a congenital skull-base defect. A meningocele contains meninges and CSF, whereas a meningoencephalocele also contains brain tissue.
Types: Nasal encephaloceles mainly occur as frontoethmoidal or basal lesions. Frontoethmoidal lesions usually present as an external midline nasal mass. Basal lesions pass through defects in the cribriform plate or sphenoid and may present as an intranasal mass, nasal obstruction or CSF rhinorrhoea.
Clinical Features: Patients usually present with a midline nasal mass. The mass may enlarge during crying, straining or Valsalva and may appear pulsatile. CSF rhinorrhoea may occur and increases the risk of meningitis.
Investigations: MRI best defines the brain tissue, CSF, tract and intracranial extension. CT demonstrates the skull-base defect. CT or MR cisternography may help localise an associated CSF leak.
Management: Treat encephaloceles with surgical repair. Use an endoscopic endonasal approach for suitable basal lesions. Large or extensive lesions may require a cranial or combined approach. ENT and neurosurgical teams should plan complex cases together.
3. Nasal Glial Heterotopia (historically called Nasal Glioma)
Nasal glioma is a benign mass of heterotopic glial tissue outside the brain. It represents a choristoma rather than a true tumour. Most lesions have no intracranial or CSF connection.
Clinical Features: Nasal gliomas usually present during infancy or early childhood as a firm, non-compressible nasal mass. The lesion may occur on the nasal bridge or inside the nasal cavity. Intranasal lesions can cause nasal obstruction. Nasal gliomas may occur externally, intranasally or at both sites. Some classic ENT series report that approximately 60% occur externally, 30% intranasally and 10% at both sites.
Diagnosis: MRI defines the soft-tissue lesion and helps assess intracranial communication. CT helps assess the skull base and bony anatomy.
Management: Perform complete surgical excision. Choose the approach according to the site and extent of the lesion. Use an external rhinoplasty or lateral nasal approach for suitable external lesions and an endoscopic endonasal approach for suitable intranasal lesions.
4. Cleft Nose
2. Hump Nose
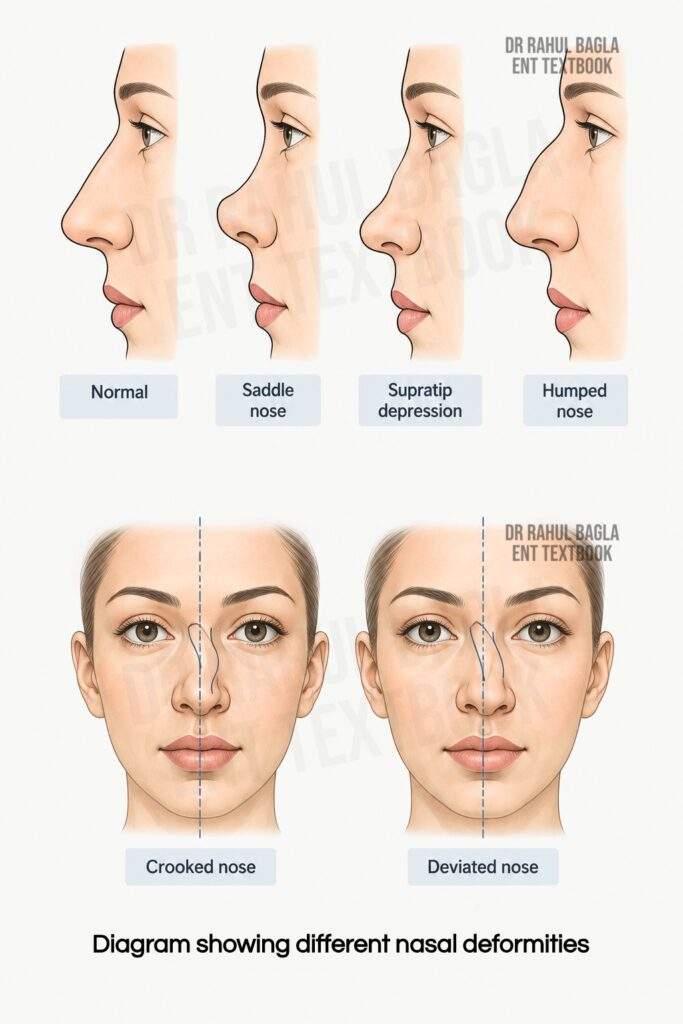
Hump nose presents as excessive bony, cartilaginous or combined prominence of the nasal dorsum. Common causes include genetic factors and trauma, which may cause post-traumatic overgrowth. A prominent dorsal hump may occur with a deviated septum, long nose or underprojected nasal tip.
Perform reduction rhinoplasty through an endonasal or open approach. Avoid excessive dorsal resection, as it can cause middle-vault collapse, inverted-V deformity or a pollybeak deformity.
3.Crooked/Deviated Nose
A crooked nose shows a curved or asymmetric dorsum, often with a C- or S-shaped deformity. A deviated nose shifts away from the facial midline. A twisted nose shows rotation or distortion of the nasal framework. Read more: Diseases of Nasal Septum
4. Nasal tip deformities
Common nasal tip deformities include bulbous, bifid, ptotic, overprojected and underprojected tips.
Infective and Inflammatory Conditions
1. Nasal Vestibulitis
Nasal vestibulitis is a superficial inflammation or infection of the nasal vestibule, which contains hair follicles.
Aetiology
- Non-infective: Nasal discharge (rhinitis, sinusitis), frequent nose-picking, dry air, excessive nose-blowing.
- Infective: Staphylococcus aureus, Streptococcus species. Herpes simplex virus can occasionally cause nasal vestibulitis.
- Predisposing factors: Nasal piercings, foreign bodies, diabetes mellitus, immunosuppression.
Clinical features: Patients usually develop pain, tenderness, redness, swelling and crusting of the nasal vestibule. Chronic vestibulitis may cause itching, recurrent crusting and painful fissures.
Treatment: For non-infective vestibulitis, apply a topical emollient such as petroleum jelly or use a mild topical corticosteroid for marked inflammation. For mild bacterial vestibulitis, apply topical mupirocin according to local guidelines and avoid nose-picking, excessive wiping and other trauma. Use systemic antibiotics when cellulitis, abscess formation or spreading infection develops. Consider culture in recurrent, severe or treatment-resistant cases. Assess for predisposing factors such as diabetes or immunosuppression.
2. Furunculosis (Boil)
Furunculosis is a localised acute infection of a hair follicle in the nasal vestibule, commonly caused by Staphylococcus aureus. Hair plucking, nose-picking, excessive nose-blowing, repeated wiping and nasal piercing can damage the follicle and allow bacterial infection.
Clinical features: Patients develop severe pain and tenderness, particularly over the nasal tip. Examination shows a localised red and swollen area in the nasal vestibule. A tender pustule or furuncle may develop and can progress to a small abscess. Severe infection may cause fever, malaise or headache.
Treatment:
- Mild furuncle (No Systemic Signs): Apply local moist heat for symptomatic relief. Use a topical antibiotic such as mupirocin 2% ointment three times daily for 5 days, or chlorhexidine with neomycin. Give paracetamol or ibuprofen for pain relief when appropriate.
- Severe furuncle (With Cellulitis or Systemic Symptoms): Use systemic antibiotics when cellulitis, systemic symptoms or spreading infection is present. Choose an appropriate anti-staphylococcal antibiotic according to local guidelines and resistance patterns. Drain a definite abscess when present. Admit the patient for intravenous antibiotics and monitoring if the infection is spreading or severe. Do not squeeze, pick or repeatedly manipulate a nasal furuncle. Infection from the nasal vestibule can spread through the valveless facial venous system and cause cavernous sinus thrombosis. Suspect cavernous sinus thrombosis if the patient develops bilateral periorbital oedema, ophthalmoplegia, visual impairment or altered sensorium.
Key Difference: Vestibulitis causes diffuse superficial inflammation of the nasal vestibule, whereas a furuncle causes a localised infection of a hair follicle and may form an abscess.
3. Cellulitis of the Nasal Skin
Nasal cellulitis is a diffuse bacterial infection of the nasal skin and subcutaneous tissue, commonly caused by Streptococcus pyogenes and Staphylococcus aureus.
Aetiology: Nasal cellulitis usually results from a primary skin infection or extension of infection from the nasal vestibule. Trauma, surgery and skin injury can also introduce infection. Diabetes mellitus and immunosuppression increase the risk.
Clinical Features: Patients develop pain, tenderness, warmth, erythema and swelling of the nasal skin. Fever and malaise may occur. Severe infection can spread to the periorbital region, cheek or deeper tissues and may rarely cause intracranial complications.
Treatment: Treat with an appropriate oral antibiotic, such as co-amoxiclav or cephalexin, according to local guidelines. Advise the patient to avoid touching or manipulating the affected area. Use intravenous antibiotics and obtain imaging when there is systemic toxicity, rapid progression, orbital involvement, deep extension or concern for complications.
4. Nasal Perichondritis
Nasal perichondritis is an infection of the perichondrium surrounding the nasal cartilage. Trauma, surgery and nasal piercing can introduce infection. Pseudomonas aeruginosa is an important causative organism, particularly after cartilage piercing.
Clinical features: Patients develop pain, tenderness, redness and swelling of the nasal tip or other cartilage-bearing areas. Untreated infection can compromise the cartilage and produce cartilage necrosis and saddle nose deformity.
Treatment: Start systemic antibiotics with appropriate antipseudomonal coverage when clinically indicated, guided by local antimicrobial protocols and culture results. Drain any abscess promptly and remove necrotic cartilage when necessary. Treat the infection early to prevent cartilage destruction and subsequent saddle nose deformity.
Benign Conditions and Tumours of the External Nose
1. Rhinophyma
Rhinophyma, traditionally called potato tumour, is a chronic phymatous enlargement of the nose characterised by sebaceous gland hyperplasia, fibrosis and hypertrophy of the soft tissues. It commonly occurs in patients with long-standing acne rosacea, particularly in older men.
Clinical Features: The nose develops pink or reddish, thickened and lobulated skin with prominent superficial blood vessels. Progressive disease produces marked enlargement of the nasal tip and alae. Patients mainly seek treatment because of cosmetic disfigurement. Large lesions can cause nasal obstruction and, rarely, interfere with vision.
Differential Diagnosis: Basal cell carcinoma, sarcoidosis
Treatment: Treat associated rosacea when present. For significant rhinophyma, perform debulking of the tumour using a scalpel, dermabrasion or laser. The area is allowed to re-epithelialize. Laser excision, particularly with a CO₂ laser, is commonly preferred because it provides precise tissue removal and good haemostasis. Avoid excessively deep excision or aggressive dermabrasion because it can impair healing and produce poor cosmetic results. Treatment may cause bleeding, infection, scarring, prolonged erythema and recurrence. Extensive full-thickness excision with skin grafting is rarely required and is generally reserved for severe disease with extensive tissue involvement, and it produces inferior cosmetic outcomes.
2. Hemangioma
Hemangiomas are benign vascular lesions that may arise from capillary or cavernous vascular tissue. They commonly occur in children and may enlarge during an early proliferative phase. Infantile hemangiomas are benign vascular tumours that usually appear during infancy and undergo a proliferative phase followed by gradual involution. Superficial lesions appear red, while deeper lesions may appear bluish or skin-coloured.
Clinical classification
- Superficial infantile hemangioma: Bright red, raised lesion.
- Deep infantile hemangioma: Bluish or skin-coloured, deeper lesion.
- Mixed: Features of both superficial and deep components.
Clinical Features: Capillary lesions usually appear as red superficial lesions, whereas cavernous lesions form deeper, soft and compressible masses. Large lesions may cause cosmetic deformity, bleeding or functional problems.
Treatment: Most uncomplicated infantile hemangiomas can be observed. Oral propranolol is the first-line systemic treatment for infantile hemangiomas requiring systemic therapy. Topical timolol may be used for selected small, thin, superficial lesions. Laser or surgery has a limited role, particularly for residual lesions or selected complications.
3. Epidermoid Cyst (Often Incorrectly Called Sebaceous Cyst)
An epidermoid cyst is a benign cyst lined by stratified squamous epithelium and filled with keratin. It usually appears as a slow-growing, skin-coloured or yellowish swelling. A central punctum may be present, and the cyst may discharge cheesy material after rupture or infection. The commonly used term “sebaceous cyst” is a misnomer because these cysts do not arise from sebaceous glands.
Treatment: Perform complete excision of the cyst with its wall. Avoid rupturing the cyst during surgery because retained cyst wall can cause recurrence.
4. Cutaneous Papilloma
A nasal papilloma is a benign epithelial proliferation, often associated with human papillomavirus (HPV). It usually presents as a papillary or verrucous exophytic lesion.
Treatment: Treat symptomatic or cosmetically significant lesions with complete surgical excision. Laser ablation or cryotherapy may be used in selected cases. Histopathological examination confirms the diagnosis.
5. Pigmented Nevus
A pigmented nevus is a benign proliferation of melanocytes. It may appear as a flat or raised, brown or black lesion and may develop during childhood or remain present from birth.
Treatment: Observe stable lesions. Excise lesions that show change in size, colour, shape or other suspicious features, or those that require treatment for cosmetic reasons. Send excised lesions for histopathological examination when indicated.
6. Seborrhoeic Keratosis
Seborrhoeic keratosis is a benign epidermal lesion that commonly affects older individuals. It appears as a well-defined, brown or black, waxy, “stuck-on” lesion.
Treatment: No treatment is required for asymptomatic lesions. Remove the lesion by excision, curettage or cryotherapy when it causes symptoms or cosmetic concern.
Malignant Tumours of External Nose
Malignant tumours of the external nose mainly include basal cell carcinoma, squamous cell carcinoma and malignant melanoma. Merkel cell carcinoma is rare but highly aggressive. Chronic ultraviolet exposure is an important risk factor for most cutaneous malignancies of the nose. Early diagnosis and appropriate treatment help achieve good local control and cosmetic outcomes.
1. Basal Cell Carcinoma (Rodent Ulcer)
Basal cell carcinoma (BCC) is the most common malignant tumour of the skin of the nose. In classic ENT textbook series, BCC accounts for about 87% and SCC about 11% of malignant tumours of the nasal skin. It commonly affects the nasal tip and ala, which are the most sun-exposed areas. It occurs mainly in middle-aged and older adults and affects males and females almost equally. It arises from basal cells of the epidermis and commonly develops on sun-exposed skin.
Aetiology: Chronic ultraviolet radiation is the most important risk factor. Fair skin, light-coloured eyes, previous radiation exposure, immunosuppression and certain genetic conditions, such as Gorlin syndrome (basal cell nevus syndrome), increase the risk.
Clinical Features: BCC usually presents as a slowly growing, painless lesion. It may appear as:
- Nodular (most common): Pearly papule or nodule with surface telangiectasia; may ulcerate with rolled, pearly edges (rodent ulcer)
- Morphoeic (sclerosing): Flat, scar-like, ill-defined; more aggressive with higher recurrence risk
- Superficial: Erythematous, scaly plaque; more common on trunk
- Pigmented: Darkly pigmented; may mimic melanoma
BCC usually grows slowly and has very low metastatic potential, but untreated lesions can cause extensive local destruction and invade the underlying cartilage or bone. The nose is considered a high-risk anatomical site because of its cosmetic importance and the need to preserve surrounding tissue during treatment.
Diagnosis: Confirm the diagnosis with a skin biopsy. Choose the biopsy technique (shave, punch or excisional biopsy) according to the size, site and suspected subtype of the lesion. Use CT or MRI when the tumour shows suspected deep invasion or involvement of cartilage, bone or nerves.
Treatment: Select treatment according to the tumour size, site, subtype, depth and risk of recurrence. Surgical excision provides effective treatment for most lesions.
- Surgical excision: Effective for most lesions; use 3–5 mm margins for low-risk lesions.
- Mohs micrographic surgery: Mohs micrographic surgery is preferred for selected high-risk BCCs, recurrent tumours and tumours in tissue-sparing anatomical sites such as the nose. It provides precise margin control while preserving normal tissue.
- Radiotherapy: For patients who cannot undergo surgery or when surgery would cause unacceptable morbidity.
- Topical therapy (imiquimod, 5-fluorouracil): It has a limited role for the nose because nasal BCCs are often considered high risk due to their anatomical location.
- Hedgehog-pathway inhibitors (vismodegib, sonidegib): Selected for locally advanced or metastatic tumours not suitable for curative surgery or radiotherapy.
Prognosis: BCC has an excellent prognosis when treated early. It has a very low metastatic potential, but untreated lesions can cause significant local tissue destruction. Regular follow-up helps detect recurrence and new skin cancers.
2. Squamous cell carcinoma
Squamous cell carcinoma (SCC) is a malignant tumour arising from keratinising squamous epithelial cells. Squamous cell carcinoma is the second most common skin malignancy of the nose. It usually grows faster and has a greater metastatic potential than basal cell carcinoma (BCC). It typically affects males and females equally in the 40–60 year age group.
Aetiology and Risk Factors: Chronic ultraviolet exposure is the most important risk factor for SCC. Actinic keratosis and Bowen disease can act as precursor lesions. Immunosuppression, chronic wounds, scars, previous radiation and certain chemical exposures can also increase the risk.
Clinical Features: SCC usually presents as an indurated nodule, plaque or ulcer with an irregular or raised margin. The lesion may show scaling, crusting or bleeding. Pain may occur, particularly in advanced lesions. Rapid growth, deep infiltration, perineural symptoms and regional lymphadenopathy suggest aggressive disease. Common sites on the nose include the side of the nose and columella. A key clinical distinction is that SCC has everted, indurated margins, whereas BCC has rolled, pearly edges. Regional lymph-node metastasis is more common than in BCC and occurs particularly in high-risk lesions. Some classic ENT series report regional nodal metastasis in approximately 20% of nasal SCCs.
Risk Assessment: Assess tumour size, depth, differentiation, anatomical site, perineural invasion and other pathological features to determine the risk of recurrence and metastasis. A tumour larger than 2 cm, deep invasion, poor differentiation and perineural invasion increase the risk, but no single factor should determine risk classification.
Diagnosis: Diagnosis of squamous cell carcinoma is confirmed with a skin biopsy, which helps assess the depth of invasion, histological differentiation and presence of perineural invasion. Use CT or MRI when the tumour shows suspected deep invasion, bone involvement or perineural spread. Assess suspicious regional lymph nodes with ultrasound, fine-needle aspiration or core biopsy as appropriate. Sentinel lymph node biopsy is not routinely recommended for all cutaneous SCCs but may be considered in selected very high-risk tumours. Chest X-ray or CT may be performed to rule out distant metastasis, though this is rare.
- Surgery: Wide local excision with 4–6 mm margins is appropriate for low-risk lesions. Cervical lymph node dissection (block dissection) is indicated for clinically positive regional lymph nodes. Advanced lesions or those with bone or cartilage involvement require wide surgical excision and plastic reconstruction of the defect.
- Mohs micrographic surgery is the gold standard for high-risk, recurrent, or cosmetically sensitive areas such as the nose, as it provides precise margin control while preserving normal tissue.
- Radiotherapy: Current guidance considers surgery the most effective treatment for cutaneous SCC, with radiation selected for particular low-risk cases, patients unsuitable for surgery, or as adjuvant treatment in selected high-risk situations.
- Topical therapy such as 5-fluorouracil or imiquimod has a limited role and is reserved for selected superficial lesions.
Prognosis: Most low-risk SCCs have a good prognosis after complete treatment. High-risk tumours have a greater risk of local recurrence, regional lymph-node metastasis and, rarely, distant metastasis. Regular follow-up is important because patients remain at risk of recurrence and new skin cancers.
Comparison table BCC vs SCC
| Feature | Basal Cell Carcinoma | Squamous Cell Carcinoma |
| Frequency | Most common skin malignancy of the nose | Second most common |
| Typical site | Tip and ala | Side of nose and columella |
| Ulcer edge | Rolled, pearly | Everted, indurated |
| Growth rate | Very slow | Faster than BCC |
| Local invasion | Can invade cartilage and bone if untreated | Can invade cartilage and bone |
| Metastasis | Extremely rare | More common than BCC |
| Risk factors | UV exposure, fair skin, immunosuppression | UV exposure, actinic damage, immunosuppression, chronic wounds/scars |
| Prognosis | Excellent when treated early | Good when detected early, but greater metastatic potential |
3. Malignant Melanoma
Malignant melanoma is an aggressive malignant tumour of melanocytes. It is less common than basal cell carcinoma and squamous cell carcinoma but has a greater risk of lymphatic and distant metastasis. Important risk factors include intermittent intense ultraviolet exposure, fair skin, family history and multiple or atypical nevi. Suspect melanoma using the ABCDE rule: Asymmetry, Border irregularity, Colour variation, Diameter >6 mm and Evolution. Melanoma may also be amelanotic and may not show all these features.
Confirm the diagnosis with an excisional biopsy with a narrow margin whenever possible. Histopathology determines the Breslow thickness and assesses ulceration. Perform wide local excision with margins based on tumour thickness. Consider sentinel lymph node biopsy for melanomas ≥0.8 mm thick or selected thinner lesions with adverse features. Advanced disease may require immunotherapy or BRAF/MEK-targeted therapy in BRAF-mutant tumours. Prognosis mainly depends on tumour thickness, ulceration, nodal involvement and distant metastasis.
4. Merkel Cell Carcinoma
Merkel cell carcinoma is a rare, aggressive neuroendocrine carcinoma of the skin. It mainly affects older adults and occurs more often in areas exposed to ultraviolet radiation and in immunosuppressed patients. It typically presents as a rapidly growing, firm, painless pink, red or violaceous nodule. The tumour can metastasise early to regional lymph nodes and distant organs.
Confirm the diagnosis with a skin biopsy and appropriate immunohistochemical studies. Stage the tumour according to local, regional and distant spread. Treat localised disease with complete surgical excision and consider sentinel lymph node biopsy for regional staging. Adjuvant radiotherapy may reduce the risk of local and regional recurrence. Advanced or unresectable disease may require immune checkpoint inhibitors, such as pembrolizumab, avelumab or retifanlimab. Prognosis depends mainly on tumour stage and lymph-node involvement.
NEET PG-Style MCQs
1. A 3-year-old child presents with a midline nasal swelling and a small sinus from which hair protrudes. Which is the most likely diagnosis? A. Encephalocele B. Nasal dermoid C. Nasal glial heterotopia D. Hemangioma
2. A congenital midline nasal mass enlarges during crying and Valsalva. Which diagnosis should be suspected most strongly? A. Dermoid cyst B. Encephalocele C. Epidermoid cyst D. Rhinophyma
3. The most useful investigation for assessing intracranial soft-tissue extension of a congenital midline nasal mass is: A. Plain radiograph B. Ultrasound C. MRI D. Diagnostic biopsy
4. A patient with a painful nasal furuncle develops fever, severe headache, periorbital oedema and ophthalmoplegia. The most important complication to suspect is: A. Orbital cellulitis B. Cavernous sinus thrombosis C. Septal hematoma D. Facial nerve palsy
5. Which organism is particularly important in perichondritis following cartilage piercing? A. Streptococcus pneumoniae B. Pseudomonas aeruginosa C. Haemophilus influenzae D. Mycoplasma pneumoniae
6. The first-line systemic treatment for a problematic infantile hemangioma requiring systemic therapy is: A. Prednisolone B. Propranolol C. Vincristine D. Doxycycline
7. Which clinical feature most strongly suggests basal cell carcinoma? A. Everted indurated margin B. Rapidly growing violaceous nodule C. Pearly nodule with surface telangiectasia D. Black lesion with multiple colours
8. Which feature is classically associated with cutaneous squamous cell carcinoma? A. Rolled pearly margin B. Everted indurated margin C. Increase in size with Valsalva D. Hair protruding from the lesion
9. A patient has a changing pigmented lesion over the external nose. Which histopathological parameter is particularly important for melanoma prognosis? A. Mitotic rate only B. Tumour colour C. Breslow thickness D. Serum calcium
10. Which statement regarding Merkel cell carcinoma is most accurate? A. It is a slowly growing tumour with negligible metastatic potential B. It is usually associated with sebaceous gland hyperplasia C. It is an aggressive cutaneous neuroendocrine carcinoma D. It is treated primarily with topical antibiotics
Answer Key: 1: B. 2: B. 3: C. 4: B. 5: B. 6: B. 7: C. 8: B. 9: C. 10: C.
Frequently Asked Questions
- What are the common diseases of the external nose? Common diseases include congenital lesions, nasal deformities, vestibulitis, furunculosis, perichondritis, rhinophyma, benign tumours and malignant skin cancers.
- What are the three major congenital midline nasal lesions? The major lesions are nasal dermoid, encephalocele and nasal glial heterotopia.
- Which nasal mass increases with crying or Valsalva? An encephalocele may enlarge with crying, straining or Valsalva because of its intracranial communication.
- What does hair emerging from a nasal sinus indicate? Hair emerging from a congenital midline nasal sinus strongly suggests a nasal dermoid.
- Which investigation is best for intracranial extension of a nasal dermoid? MRI is particularly useful for assessing soft tissue, sinus tracts, intracranial extension and dural relationships. CT complements MRI by defining bony anatomy.
- What is the difference between nasal vestibulitis and furunculosis? Vestibulitis is superficial inflammation or infection of the nasal vestibular skin, whereas furunculosis is a localized infection of a hair follicle that may form an abscess.
- What is the dangerous complication of nasal furunculosis? Cavernous sinus thrombosis is the classic serious intracranial complication of infection spreading from the nasal vestibule.
- What causes saddle nose deformity? Important causes include trauma, excessive septal cartilage removal, granulomatosis with polyangiitis, relapsing polychondritis, sarcoidosis and selected infections.
- How can BCC and SCC of the nose be differentiated? BCC typically has a pearly appearance with surface telangiectasia and rolled edges, whereas SCC commonly has an indurated, crusted or ulcerated appearance with an everted margin.
- What is the first-line systemic treatment for problematic infantile hemangioma? Oral propranolol is the first-line systemic treatment for infantile hemangiomas requiring systemic therapy.
-——— End of the chapter ————
Reference Textbooks.
- Scott-Brown, Textbook of Otorhinolaryngology-Head and Neck Surgery.
- Cummings, Otolaryngology-Head and Neck Surgery.
- Stell and Maran’s, Textbook of Head and Neck Surgery and Oncology.
- Ballenger’s, Otorhinolaryngology Head And Neck Surgery
- P L Dhingra, Textbook of Diseases of Ear, Nose and Throat.
- Hazarika P, Textbook of Ear Nose Throat And Head Neck Surgery Clinical Practical.
- Mohan Bansal, Textbook of Diseases of Ear, Nose and Throat Head and Neck Surgery.
- Logan Turner, Textbook of Diseases of The Nose, Throat and Ear Head And Neck Surgery.
Author:

Dr. Rahul Bagla
MBBS (MAMC, Delhi) MS ENT (UCMS, Delhi)
Fellow Rhinoplasty & Facial Plastic Surgery.
Renowned Teaching Faculty
Mail: msrahulbagla@gmail.com
India
Please read. Glomus Tumour. https://www.entlecture.com/glomus-tumour/
Follow our Facebook page: https://www.facebook.com/Dr.Rahul.Bagla.UCMS
Join our Facebook group: