
|
The following CBME core competencies are covered in this chapter.
|
Acute Rhinitis
Introduction
Acute rhinitis is an acute inflammation of the nasal mucosa, most commonly caused by viral infection and presenting with sneezing, rhinorrhoea, nasal obstruction, and nasal irritation. The common cold is the most frequent form of acute viral rhinitis and is usually caused by respiratory viruses, particularly rhinoviruses.
Most cases are self-limiting and improve with supportive and symptomatic treatment. Nasal discharge may change from clear to mucoid or discoloured during the illness and does not, by itself, indicate bacterial infection. Symptoms that persist for more than 10 days without improvement, become severe, or worsen after initial improvement should raise suspicion for acute bacterial rhinosinusitis rather than uncomplicated viral rhinitis.
This chapter covers the causes, classification, pathogenesis, stages, clinical features, diagnosis, differential diagnosis, complications, and treatment of acute rhinitis, along with CBME-based notes, high-yield revision points, viva questions, clinical cases, and NEET PG-style MCQs.
Types of Acute Rhinitis
Acute rhinitis is usually classified by its underlying cause. Three main types are recognised:
- Viral rhinitis (Common cold, Influenzal rhinitis, Rhinitis associated with exanthemas)
- Bacterial rhinitis
- Irritative rhinitis
Among these, viral rhinitis is the most common type, and it usually presents as the common cold.
Viral Rhinitis
A. Common Cold (Coryza)
The common cold, also known as coryza, represents the most frequent form of acute rhinitis. It occurs when respiratory viruses infect the nasal epithelial lining. The infection produces inflammation of the mucosa, which leads to the typical symptoms of sneezing, nasal blockage, and nasal discharge.

Aetiology. Several viruses can produce acute rhinitis, and rhinovirus is the most common cause. Rhinoviruses belong to the picornavirus family, and they account for approximately half of all cases of the common cold. Other viruses that can cause acute rhinitis include coronavirus, influenza virus, parainfluenza virus, respiratory syncytial virus, adenovirus, and enterovirus. The incubation period, which is the time between infection and the appearance of symptoms, usually ranges from 1 to 4 days. After symptoms appear, the illness generally lasts for 7 to 14 days, although mild symptoms such as nasal blockage or discharge may sometimes continue for two to three weeks.
Mode of Transmission. Respiratory viruses spread mainly through respiratory particles and direct or indirect contact with infected secretions. Hand washing and avoiding contact with infected individuals reduce transmission.
Pathogenesis. After entering the nasal cavity, the virus attaches to and invades the epithelial cells of the nasal mucosa. The infected cells then release inflammatory mediators, which produce several changes in the nasal mucosa. These changes include vasodilatation of blood vessels, swelling of the mucosa, and increased secretion from seromucinous glands. As a result of these inflammatory changes, the patient develops the classic symptoms of acute rhinitis, namely nasal obstruction, rhinorrhoea, and sneezing.
Stages of Acute Viral Rhinitis
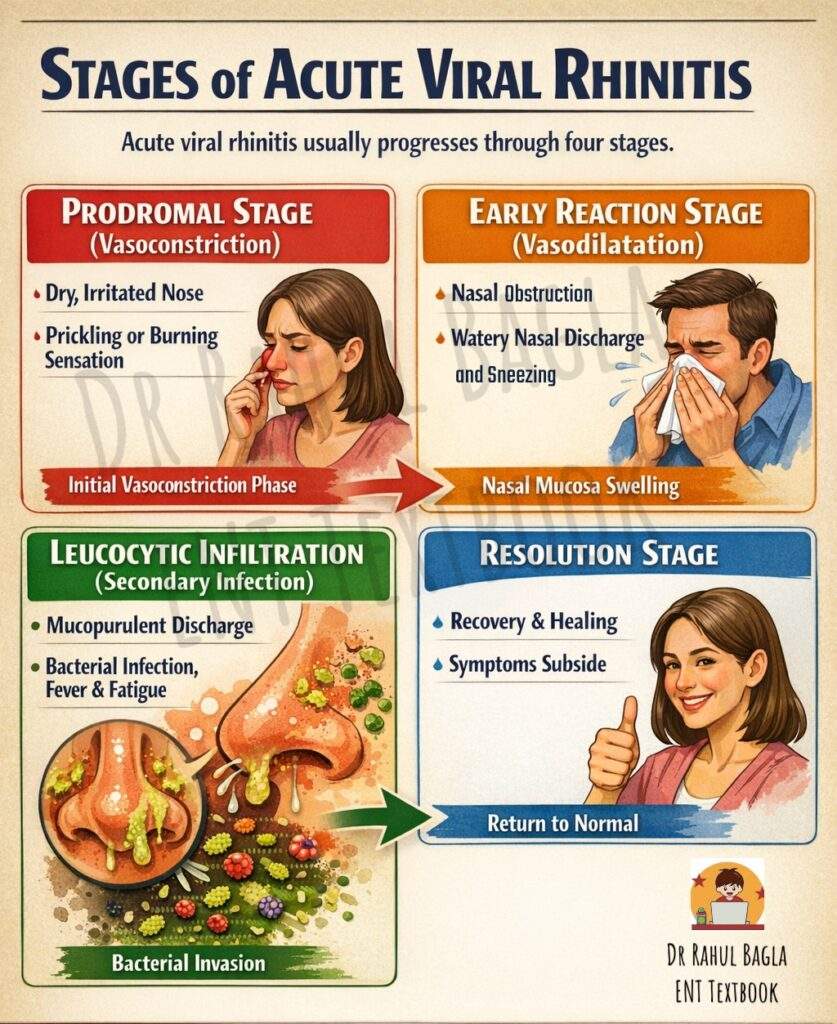
Acute viral rhinitis usually progresses through four stages. Understanding these stages is important because they are frequently asked in ENT theory examinations, viva questions, and NEET PG MCQs.
- Stage 1: Prodromal Stage (Stage of Vasoconstriction). The disease usually begins with a prodromal phase. During this stage, there is temporary vasoconstriction of the nasal blood vessels. The patient experiences a dry and irritated sensation inside the nose. Many patients also complain of a prickling or burning feeling at the back of the nose. Because these symptoms appear before the full disease develops, this phase is called the prodromal stage.
- Stage 2: Stage of Early Reaction (Stage of Vasodilatation). After the initial stage, the inflammatory process produces vasodilatation of the nasal blood vessels. This causes swelling of the nasal mucosa and increased activity of the seromucinous glands. Consequently, the patient develops nasal obstruction and profuse watery nasal discharge. Sneezing is also common during this stage.
- Stage 3: Stage of Leucocytic Infiltration (Secondary Infection Stage). During this stage, the patient usually experiences maximum nasal obstruction, general weakness, and systemic symptoms such as malaise or fever. During the later phase of viral rhinitis, inflammatory cells infiltrate the nasal mucosa. This stage does not necessarily indicate secondary bacterial infection. Bacterial rhinosinusitis is suspected when symptoms persist beyond 10 days without improvement, are severe, or worsen after initial improvement. During the later phase of viral rhinitis, the inflammatory cellular response may become more prominent, and nasal discharge may become mucoid or discoloured. Discoloured nasal secretions do not necessarily indicate bacterial infection. Common bacteria responsible for secondary infection include Haemophilus influenzae, Staphylococcus aureus, Streptococcus pyogenes (Group A beta-hemolytic streptococcus), Streptococcus pneumoniae, Moraxella catarrhalis, and Klebsiella pneumoniae.
- Stage 4: Stage of Resolution. Eventually, the body’s immune system eliminates the infection. As the inflammation subsides, the nasal mucosa gradually returns to normal. Symptoms usually improve within four to ten days, although mild nasal discharge may persist for a short period.
Clinical Features. Acute rhinitis produces both local nasal symptoms and systemic symptoms.
- Local Symptoms. The disease usually begins with a burning sensation or irritation inside the nose. Soon afterwards, the patient develops nasal stuffiness, sneezing, and rhinorrhoea. At first, the nasal discharge is clear and watery; after a few days, it may become thick and mucopurulent due to secondary bacterial infection.
- Systemic Symptoms. In addition to nasal symptoms, many patients experience general systemic features. These commonly include mild fever, chills, headache, malaise, and generalised body aches. These symptoms occur because viral infection produces a systemic inflammatory response.
Complications. In most patients, acute rhinitis resolves spontaneously within two to three weeks. However, in some cases, the infection may spread to adjacent structures and produce complications. Common complications include sinusitis, pharyngitis, tonsillitis, nasopharyngitis, lower respiratory tract infection, lymphadenitis, pneumonia, and otitis media. Rare but serious complications include cavernous sinus thrombosis. Among these complications, sinusitis and otitis media occur most frequently because inflammation in the nasal cavity may obstruct the sinus ostia or the Eustachian tube.
Investigations. Acute rhinitis is usually diagnosed clinically. Investigations are not routinely required in uncomplicated cases. Nasal swab may be performed for viral culture or PCR in severe or atypical cases. Nasal smear may show neutrophils in bacterial infection. Blood tests such as CBC may show leukocytosis in secondary bacterial infection. CT of paranasal sinuses is indicated only if sinusitis is suspected.
Differential Diagnosis. Allergic rhinitis presents with itching, sneezing, and clear discharge, with positive allergy testing. Vasomotor rhinitis presents with non-specific triggers and negative allergy testing. Acute sinusitis presents with facial pain, purulent discharge, and fever. Atrophic rhinitis presents with foul smell, crusting, and a roomy nasal cavity.
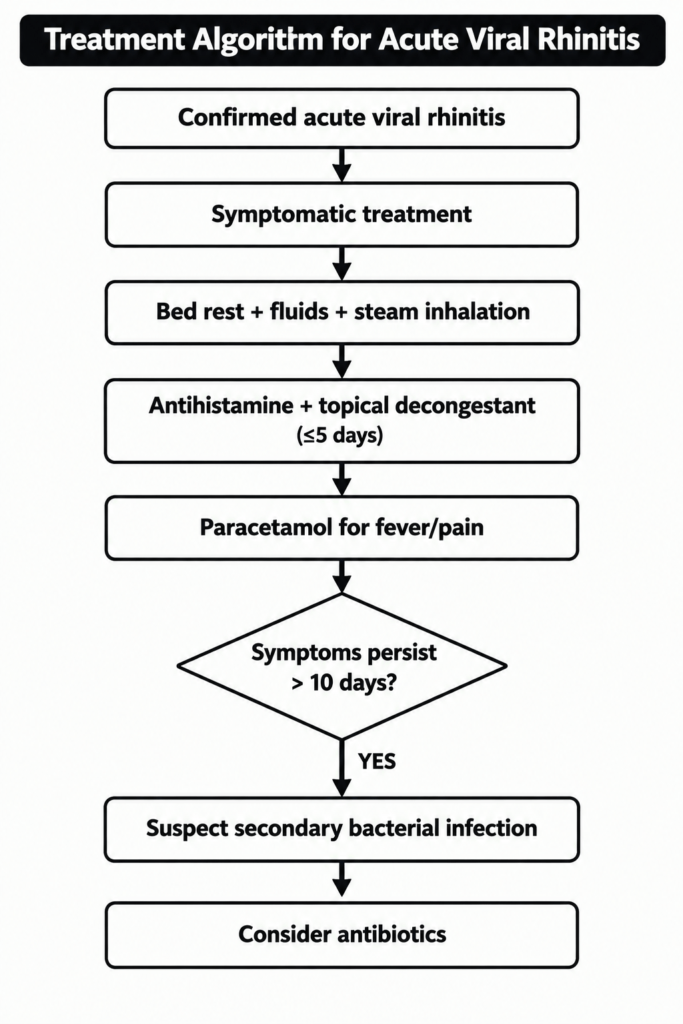
Treatment. The treatment of acute viral rhinitis is mainly symptomatic, because the disease is usually self-limiting.
- Adequate bed rest and sufficient fluid intake help improve the patient’s general condition and support the body’s natural immune response. Warm fluids and humidified air may provide subjective symptomatic relief, although evidence for steam inhalation is limited.
- Antihistamines are often prescribed because they help reduce sneezing and nasal discharge. Topical nasal decongestants may be used to decrease mucosal swelling and relieve nasal obstruction. However, they should be limited to 3–5 days to avoid rhinitis medicamentosa (rebound congestion).
- Analgesics such as paracetamol are useful for relieving fever, headache, and muscle pain. Aspirin is avoided in children with viral illness due to the risk of Reye’s syndrome; non-aspirin analgesics are preferred.
- Antibiotics are not routinely required in uncomplicated viral rhinitis. Persistence of symptoms beyond 10 days without improvement may suggest acute bacterial rhinosinusitis. In such cases, antibiotics may be considered. However, watchful waiting or delayed prescribing is appropriate in selected uncomplicated cases.
Prevention. Frequent hand washing helps reduce transmission. Avoid touching the face with unwashed hands. Avoid close contact with infected individuals. Maintain good indoor ventilation. Avoid known irritants such as smoke, dust, and chemicals. Influenza vaccination is recommended for high-risk groups.
B. Influenzal Rhinitis
Rhinitis may occur during infection with influenza viruses. Influenza is distinguished from the common cold by abrupt onset, high fever, marked systemic toxicity, myalgia, headache, and prominent respiratory symptoms. Secondary bacterial infections are more common in influenza. Patients with suspected influenza who are at increased risk (elderly, immunocompromised, chronic lung disease) may benefit from early antiviral therapy such as oseltamivir.
C. Rhinitis Associated with Exanthematous Diseases
Some viral illnesses that produce skin rashes (exanthematous diseases) also cause rhinitis in the early stage of the illness. Important examples include Measles, Rubella, and Chickenpox. In these diseases, rhinitis usually appears before the characteristic skin rash. In measles, coryza is a prominent early symptom and appears before the rash develops. In rubella, patients may develop mild rhinitis during the initial stage of the illness. In chickenpox, nasal symptoms may also occur before the appearance of the skin lesions. Typically, rhinitis develops two to three days before the skin rash. Therefore, the presence of rhinitis during the early phase of these infections can act as an important early clinical sign of the disease.
Bacterial Rhinitis
Bacterial rhinitis may occur as a primary infection or as a secondary infection following viral rhinitis.
- Primary bacterial rhinitis occurs mainly in children. It is commonly caused by bacteria such as Streptococcus pneumoniae, Streptococcus pyogenes, and Staphylococcus aureus. In some patients, a greyish-white, thick membrane may form inside the nasal cavity. When a clinician attempts to remove this membrane, bleeding may occur because the underlying nasal mucosa is inflamed.
- Secondary bacterial rhinitis develops when bacteria infect the nasal mucosa during a viral infection such as the Common Cold. It usually appears during the later stage of acute viral rhinitis, when the damaged nasal mucosa becomes more susceptible to bacterial invasion.
Diphtheritic Rhinitis
Diphtheritic rhinitis refers to nasal infection caused by Corynebacterium diphtheriae and is a manifestation of Diphtheria. This condition has become rare because of widespread vaccination, but it remains clinically important. Nasal diphtheria may occur as a primary infection in the nose or may develop secondarily after infection of the throat, known as faucial diphtheria. A greyish pseudomembrane usually covers the inferior turbinate and the floor of the nasal cavity. This membrane is thick and firmly attached to the mucosa. When clinicians attempt to remove it, bleeding usually occurs. Patients may also develop excoriation of the anterior nares and the upper lip because of the irritating nasal discharge.
Management includes strict isolation of the patient, administration of diphtheria antitoxin, and treatment with systemic antibiotics such as Penicillin.
Table: Differences between Viral and Bacterial Rhinitis
| Feature | Acute Viral Rhinitis | Acute Bacterial Rhinosinusitis |
| Typical onset | Gradual | Often follows viral URI |
| Duration | Usually improves within 7–10 days | Persistent >10 days without improvement may suggest bacterial disease |
| Nasal discharge | Clear, mucoid, or discoloured | Purulent or discoloured may occur |
| Fever | Usually absent or low-grade | May occur, especially in severe disease |
| Facial pain/pressure | Usually mild or absent | More suggestive when severe or localized |
| Course | Gradual improvement | Persistent, severe, or worsening after initial improvement |
| Antibiotics | Not indicated | Consider when bacterial rhinosinusitis is diagnosed |
Irritative Rhinitis
Irritative rhinitis occurs when the nasal mucosa is exposed to irritating environmental or chemical substances. Common irritants include dust, smoke, ammonia fumes, formalin vapors, and acidic gases. Trauma to the nasal mucosa during intranasal procedures or during removal of a nasal foreign body may also lead to irritative rhinitis.
These irritants produce an immediate catarrhal reaction in the nasal mucosa. As a result, the patient develops sneezing, nasal discharge, and nasal congestion. In many cases, the symptoms improve quickly once the irritant is removed. However, if the nasal epithelium becomes damaged, the symptoms may continue for several days.
——– End of the Chapter——–
High-Yield Points for Exams
- Rhinovirus is the most common cause of the common cold and belongs to the picornavirus family.
- The incubation period of acute viral rhinitis is 1–4 days, and the illness usually lasts 7–14 days.
- The four stages of acute viral rhinitis are Prodromal (vasoconstriction) → Early reaction (vasodilation) → Leucocytic infiltration (secondary bacterial infection) → Resolution.
- Nasal discharge changes from clear and watery (viral) to thick and mucopurulent (secondary bacterial infection).
- Antibiotics are not routinely indicated in uncomplicated viral rhinitis; they are reserved for secondary bacterial infection.
- The most common complications of acute rhinitis are sinusitis and otitis media.
- Aspirin is avoided in children with viral illness due to the risk of Reye’s syndrome.
- Diphtheritic rhinitis is characterised by a greyish pseudomembrane on the inferior turbinate that bleeds on attempted removal.
- Topical nasal decongestants should be limited to 3–5 days to avoid rhinitis medicamentosa (rebound congestion).
- Irritative rhinitis is caused by environmental irritants such as dust, smoke, and chemicals, and usually resolves once the irritant is removed.
NEET PG Style MCQs
- The most common causative agent of the common cold is: A. Influenza virus B. Rhinovirus C. Adenovirus D. Parainfluenza virus.
- The incubation period of acute viral rhinitis is: A. 12 hours B. 1–4 days C. 7 days D. 14 days.
- Mucopurulent nasal discharge in acute rhinitis typically appears during which stage? A. Prodromal stage B. Early reaction stage C. Leucocytic infiltration stage D. Resolution stage.
- A 25-year-old male presents with 3 days of sneezing, clear rhinorrhoea, and nasal obstruction without fever. The most appropriate management is: A. Antibiotics B. Antihistamine and topical decongestant C. Oral steroids D. CT scan of paranasal sinuses.
- Which of the following is the most common complication of acute rhinitis? A. Sinusitis B. Meningitis C. Laryngitis D. Epiglottitis.
- Rhinovirus belongs to which virus family? A. Picornavirus B. Orthomyxovirus C. Paramyxovirus D. Retrovirus.
- Aspirin is avoided in children with viral rhinitis because it increases the risk of: A. Bleeding B. Reye’s syndrome C. Hypertension D. Sedation.
- Coryza preceding the appearance of a skin rash is typical of which exanthematous disease? A. Measles B. Tuberculosis C. Typhoid D. Cholera.
- A greyish pseudomembrane on the inferior turbinate that bleeds on removal is characteristic of: A. Allergic rhinitis B. Atrophic rhinitis C. Diphtheritic rhinitis D. Vasomotor rhinitis.
- Which medication is most effective for reducing nasal mucosal edema in acute rhinitis? A. Antihistamine B. Topical nasal decongestant C. Antibiotic D. Antacid.
Answer Key: 1: B. 2: B. 3: C. 4: B. 5: A. 6: A. 7: B. 8: A. 9: C. 10: B.
Case-Based Scenario Questions
Case 1. A 30-year-old male presents with 3 days of sneezing, clear rhinorrhoea, and nasal obstruction. He has no fever or facial pain.
Most likely diagnosis: Acute viral rhinitis (common cold).
Best management: Symptomatic treatment with antihistamine and topical decongestant (limited to 3–5 days), bed rest, fluids, and steam inhalation.
Case 2. A 6-year-old child presents with 8 days of nasal obstruction, thick yellow nasal discharge, fever, and facial pain over the maxillary region.
Most likely diagnosis: Acute bacterial sinusitis (secondary to viral rhinitis).
Best next step: Prescribe appropriate antibiotics and consider CT of paranasal sinuses if symptoms persist.
Case 3. A 4-year-old child presents with a greyish-white membrane on the inferior turbinate. When the clinician attempts to remove it, bleeding occurs.
Most likely diagnosis: Diphtheritic rhinitis.
Best management: Strict isolation, diphtheria antitoxin, and systemic antibiotics such as penicillin.
Case 4. A 45-year-old female presents with recurrent episodes of acute rhinitis, 5–6 times per year.
Most likely underlying factors to evaluate: Allergy testing, immunodeficiency, and structural nasal obstruction (e.g., deviated septum, polyps).
Frequently asked questions in Viva
- What is the most common cause of acute rhinitis? Rhinovirus, which belongs to the picornavirus family and accounts for approximately 50% of all cases of the common cold.
- What are the four stages of acute viral rhinitis? Stage 1: Prodromal stage (vasoconstriction) → Stage 2: Early reaction stage (vasodilatation) → Stage 3: Leucocytic infiltration stage (secondary bacterial infection) → Stage 4: Resolution stage.
- How do you differentiate viral rhinitis from bacterial rhinitis? Viral rhinitis presents with clear watery discharge, low-grade or no fever, gradual onset, and duration of 7–14 days. Bacterial rhinitis presents with thick purulent yellow or green discharge, high-grade fever, facial pain, and symptoms persisting beyond 10 days or worsening after initial improvement.
- What are the common complications of acute rhinitis? Sinusitis and otitis media are the most common. Other complications include pharyngitis, tonsillitis, nasopharyngitis, lower respiratory tract infection, lymphadenitis, pneumonia, and cavernous sinus thrombosis.
- Why is aspirin avoided in children with viral rhinitis? Aspirin is avoided in children and adolescents with viral illness because it increases the risk of Reye’s syndrome, a rare but potentially fatal condition causing acute encephalopathy and hepatic dysfunction.
- What is the treatment of acute viral rhinitis? Treatment is mainly symptomatic and includes bed rest, adequate fluid intake, warm fluids, steam inhalation, antihistamines, topical nasal decongestants (limited to 3–5 days), and analgesics such as paracetamol. Antibiotics are not routinely required unless secondary bacterial infection develops.
- What is diphtheritic rhinitis and how is it managed? Diphtheritic rhinitis is a nasal infection caused by Corynebacterium diphtheriae, characterised by a greyish pseudomembrane on the inferior turbinate that bleeds on attempted removal. Management includes strict isolation, diphtheria antitoxin, and systemic antibiotics such as penicillin.
- What is rhinitis medicamentosa? Rhinitis medicamentosa is rebound nasal congestion caused by prolonged or excessive use of topical nasal decongestants, typically after more than 3–5 days of continuous use.
- What is the incubation period of the common cold? The incubation period is 1–4 days.
- When would you refer a patient with acute rhinitis to an ENT specialist? Referral is indicated when symptoms persist beyond 10 days despite treatment, when there is severe facial pain or swelling, orbital involvement, neurological symptoms, recurrent episodes (more than 5 per year), or unilateral symptoms with epistaxis.
——– End——–
Reference Textbooks.
- Scott-Brown, Textbook of Otorhinolaryngology-Head and Neck Surgery.
- Cummings, Otolaryngology-Head and Neck Surgery.
- Stell and Maran’s, Textbook of Head and Neck Surgery and Oncology.
- Ballenger’s, Otorhinolaryngology Head And Neck Surgery
- P L Dhingra, Textbook of Diseases of Ear, Nose and Throat.
- Hazarika P, Textbook of Ear Nose Throat And Head Neck Surgery Clinical Practical.
- Mohan Bansal, Textbook of Diseases of Ear, Nose and Throat Head and Neck Surgery.
- Hans Behrbohm, Textbook of Ear, Nose, and Throat Diseases With Head and Neck Surgery.
- Logan Turner, Textbook of Diseases of The Nose, Throat and Ear Head And Neck Surgery.
- Arnold, U. Ganzer, Textbook of Otorhinolaryngology, Head and Neck Surgery.
Author:

Dr. Rahul Bagla
MBBS (MAMC, Delhi) MS ENT (UCMS, Delhi)
Fellow Rhinoplasty & Facial Plastic Surgery.
Renowned Teaching Faculty
Mail: msrahulbagla@gmail.com
India
———– Follow us on social media ————
- Follow our Facebook page: https://www.facebook.com/Dr.Rahul.Bagla.UCMS
- Follow our Instagram page: https://www.instagram.com/dr.rahulbagla/
- Subscribe to our Youtube channel: https://www.youtube.com/@Drrahulbagla
- Please read. Anatomy of External Ear. https://www.entlecture.com/anatomy-of-ear/
- Please read. Anatomy of Temporal Bone. https://www.entlecture.com/anatomy-of-temporal-bone/
- Please read. Stenger’s, Chimani Moos, Teal test. https://www.entlecture.com/special-tuning-fork-tests/
Keywords: Acute Rhinitis Ent Notes For Mbbs Students, Acute Rhinitis Exam Guide For Neet Pg Preparation, Acute Rhinitis Stages Explained For Medical Students, Acute Rhinitis Pathophysiology Simplified Ent Notes, Acute Rhinitis Clinical Features Diagnosis And Treatment Notes, Acute Rhinitis Complications Sinusitis Otitis Media Ent Guide, Acute Rhinitis Mnemonics Mcqs And Revision Notes, Acute Rhinitis Cbme Curriculum Ent Study Guide, Acute Rhinitis Viva Questions For Ent Practical Exam, Acute Rhinitis Quick Revision Notes For Medical Entrance Exams, Acute Rhinitis Viral Vs Bacterial Rhinitis Differences, Acute Rhinitis Summary For Mbbs And Pg Students, Acute Rhinitis Exam Preparation Notes For Indian Medical Students