
Diseases of the Nasal Septum – MBBS & ENT PG Notes
Introduction
Diseases of the nasal septum are important ENT topics for MBBS, ENT PG, NEET PG, INI-CET and FMGE examinations. The major septal disorders include deviated nasal septum (DNS), septal hematoma, septal abscess and septal perforation. These conditions may present with nasal obstruction, epistaxis, pain, crusting, whistling, recurrent infection or external nasal deformity.
This chapter provides complete nasal septum notes covering causes, types, clinical features, examination, diagnosis and management. It also includes high-yield revision points, clinical cases, viva questions and NEET PG-style MCQs for rapid exam preparation.
A deviated septum is common and does not require treatment simply because the septum is not perfectly straight. Management depends on symptoms, functional obstruction, associated nasal pathology and the overall clinical examination. In contrast, a septal hematoma is an ENT emergency because delayed drainage can cause cartilage necrosis and saddle-nose deformity.
For revision, remember the three major clinical problems: DNS causes obstruction, septal hematoma causes acute bilateral swelling after trauma, and septal perforation causes crusting, epistaxis and sometimes whistling.
Anatomy of the Nasal Septum
The nasal septum forms the central partition of the nasal cavity and divides it into right and left nasal passages. Structurally, it consists of septal cartilage anteriorly, the perpendicular plate of the ethmoid superiorly, and the vomer inferiorly and posteriorly. Functionally, the septum contributes to the separation and direction of nasal airflow, nasal support, and conditioning of inspired air. Septal pathology can affect nasal airflow and, depending on its location and severity, may contribute to nasal obstruction, altered nasal physiology, or external nasal deformity. Read more on: 🔗Anatomy of Nasal Septum

Diseases of the nasal septum are commonly present in outpatient ENT practice and frequently appear in university theory examinations, practical examinations, viva voce, and NEET PG multiple-choice questions. Among these, Deviated Nasal Septum (DNS), septal hematoma, and septal perforation represent the most clinically important and exam-relevant conditions.
Deviated Nasal Septum (DNS)
Deviated nasal septum is the most common structural cause of nasal obstruction encountered in ENT practice. It is present in a significant proportion of the general population, but only symptomatic deviation requires intervention.
Definition. A deviated nasal septum refers to the displacement of the septum from the midline, resulting in asymmetry between the two nasal cavities. Depending on its severity and location, a deviated septum may contribute to unilateral or bilateral nasal obstruction.
Causes
1.Developmental / Racial Causes
- During growth, disproportionate development between the septum and surrounding facial bones may cause bending or buckling.
- Genetic predisposition. A family history of DNS can sometimes be elicited.
2. Trauma
- Childhood injury. In many adults, the deviation originates from childhood trauma, although patients often fail to recall such injury. Thus, when you evaluate a patient with DNS, always enquire about childhood injury, even if the patient initially denies trauma.
- Accidental trauma. Such as falls, sports injuries, road traffic accidents, or physical assault, also contribute significantly.
- Birth trauma. During prolonged labour, the nasal cartilage may be compressed and lead to later deviation.
Types of Septal Deviation (Morphological Classification)

Septal deviation presents in characteristic patterns.
- C-shaped deviation is the most common type. In this condition, the septum bends to one side, forming a single curve. The nasal cavity on the concave side becomes wider. As a result, the turbinate on that side may enlarge to compensate, which is called compensatory hypertrophy.
- S-shaped deviation shows double curvature. The septum bends in two opposite directions. This deformity may occur in the vertical plane or in the anteroposterior plane. Since both nasal cavities become narrow at different levels, the patient may develop bilateral nasal obstruction.
- Septal spur is a sharp projection usually seen at the junction of cartilage and bone. The spur may press against the lateral nasal wall. Because of this pressure, the patient may complain of nasal obstruction, recurrent epistaxis, or even headache.
- Septal thickening refers to localised enlargement of the septum. This thickening may occur due to an organised hematoma or overlapping of fractured septal fragments after trauma.
- Caudal dislocation means forward displacement of the lower end of the septum into one nasal cavity. This type is commonly visible on anterior rhinoscopy and may cause visible nasal deformity.
In practical examinations, examiners commonly ask you to identify the type of deviation on anterior rhinoscopy. Therefore, always describe the direction, location, and extent of deviation clearly.
Clinical Features
- Nasal Obstruction. This is the most common symptom. It may be unilateral or bilateral, depending on the severity and type of deviation. The degree of nasal obstruction depends on the site, severity and configuration of the deviation, as well as associated turbinate or nasal valve pathology. Importantly, constant obstruction usually indicates structural blockage, such as DNS. In contrast, intermittent obstruction suggests mucosal causes such as turbinate hypertrophy or allergic rhinitis. When obstruction changes sides periodically, the nasal cycle likely explains the symptom. Decongestant Test. A simple bedside method helps differentiate structural from mucosal causes. Improvement after decongestion suggests a significant reversible mucosal component, whereas persistent obstruction suggests a structural component. Many patients have both structural and mucosal contributors. This clinical reasoning often appears in NEET PG MCQs.
- Epistaxis. Patients, especially those with a septal spur, may develop recurrent nosebleeds. The spur stretches and thins the mucosa, leading to crust formation. When the crust is removed, bleeding occurs.
- Headache. A septal spur or marked septal deviation may contact the lateral nasal wall and, in selected patients, be associated with facial pain or headache, sometimes described as Sluder’s neuralgia. However, the relationship between septal contact and headache is not always causal, and contact-point headache remains a controversial diagnosis.
- Recurrent Sinusitis. DNS may block sinus openings and interfere with normal drainage and ventilation. As a result, patients may experience recurrent sinus infections.
- Anosmia or Hyposmia. Severe deviation may prevent inspired air from reaching the olfactory area, leading to partial or complete loss of smell.
- External nasal deformity. Significant septal deformity may be associated with deviation of the nasal dorsum, tip, or columella, producing visible cosmetic deformity.
- Associated symptoms. May include mouth breathing, sleep disturbance and reduced quality of life, depending on the severity of obstruction.
Examination and Diagnosis
- Anterior Rhinoscopy. It allows direct visualisation of deviation (to identify type, site, and direction of deviation), spur, thickening, or caudal dislocation. However, posterior deviations and associated conditions require diagnostic nasal endoscopy. Always perform this before and after decongestion to assess the mucosal component.
- Diagnostic Nasal Endoscopy (DNE). Endoscopy also helps detect polyps, turbinate hypertrophy, sinus disease, or adenoid enlargement. When examining a patient with nasal obstruction, always identify the exact site of obstruction. It may occur at the vestibule, nasal valve, attic region (upper septum), turbinate region, or choana. Posterior causes, such as a choanal polyp, may be missed without endoscopy.
- CT Scan (PNS). Not routine but used for complex cases, sinusitis, or pre-op planning. Shows the relationship of the deviation to the sinuses. Ordered by the surgeon; not a first-line diagnostic test.
- Cottle’s test evaluates the internal nasal valve. When you gently pull the cheek laterally, the nasal valve area widens. If airflow improves, the test is positive and indicates obstruction at the level of the internal nasal valve. This area offers maximum resistance to airflow and therefore plays a crucial role in nasal physiology.

Grading and Clinical Significance
Clinical grading. Septal deviation can be clinically categorised into:
- Asymptomatic deviation: No clinically significant nasal obstruction; treatment is usually unnecessary.
- Symptomatic deviation: Causes functional nasal obstruction or other symptoms.
- Severe/impacted deviation: Markedly narrows the nasal passage and may contact the lateral nasal wall.
Mladina’s Classification. Mladina classified septal deformities into seven types based on rhinoscopic or radiological findings. These include mild vertical deviation (Type I), anterior vertical deviation (Type II), posterior vertical deviation (Type III), S-shaped deformity (Type IV), horizontal crest (Type V), maxillary crest deformity (Type VI), and combination deformities (Type VII).
Management
Management depends entirely on symptoms. Asymptomatic deviation requires no treatment. However, symptomatic cases require surgical correction. 🔗Septoplasty remains the preferred procedure because it preserves the septal framework while correcting deviation. In contrast, 🔗Submucosal resection (SMR) removes larger portions of cartilage and bone and therefore carries a greater risk of complications such as septal perforation or saddle nose deformity. Modern practice strongly favours septoplasty over SMR.
Table: Differences between Septoplasty and Submucosal Resection
| Feature | Septoplasty (The Modern Choice) | Submucosal Resection (SMR) (Historical) |
| Principal | Preserve and Reconstruct. Only the most deviated parts are removed, reshaped, or repositioned. | Resect and Remove. Most of the quadrangular cartilage and bone are removed. |
| Cartilage Removal | Minimal. The L-strut (dorsal and caudal strip) is preserved for structural support. | Extensive. The central part of the cartilage is removed, leaving supporting dorsal and caudal portions. |
| Indications | Preferred technique for most symptomatic septal deviations, with technique tailored to the site and severity of deformity. | Historical technique. Limited use in contemporary practice, with selected applications depending on the deformity and surgical access required. |
| Complications | Generally lower risk of structural support loss when adequate septal support is preserved. | Greater risk of septal perforation and saddle nose deformity if excessive cartilage or structural support is removed. |
High-Yield Surgical Tip: In septoplasty, preserve an adequate L-strut of cartilage along the dorsal and caudal septum, commonly taught as approximately 1–1.5 cm. This structural support is essential for maintaining the nasal dorsum and tip and preventing postoperative deformity.
Septal Hematoma and Abscess
Definition
Septal hematoma is an acute collection of blood between the septal cartilage and its overlying mucoperichondrium. When infected, it progresses to a septal abscess. Both are ENT emergencies requiring urgent drainage to prevent cartilage necrosis and saddle-nose deformity.
Pathophysiology
The septal cartilage derives its nutrition entirely from the overlying perichondrium. During trauma, submucosal vessels rupture and blood accumulates between cartilage and mucoperichondrium. Persistent separation of the mucoperichondrium compromises the nutrition of the septal cartilage and can lead to cartilage necrosis over the ensuing days. Moreover, stagnant blood provides an excellent medium for bacterial growth, which may lead to a septal abscess. Therefore, early recognition and drainage are essential to prevent complications.
Etiology
- Trauma (Most common). Sports injuries, roadside accidents, falls, and assault.
- Iatrogenic. After septoplasty, Submucous resection (SMR), Functional endoscopic sinus surgery (FESS)
- Atraumatic (Less common). Bleeding disorders, Anticoagulant therapy, Spontaneous vascular rupture.
Clinical Presentation.
Patients usually present soon after nasal trauma.
Symptoms
- Bilateral nasal obstruction (most common symptom)
- Nasal pain
- Frontal headache
- Pressure over the nasal bridge
- Rhinorrhoea
- Fever (if infection develops)
Signs (Anterior Rhinoscopy). Typical findings include:
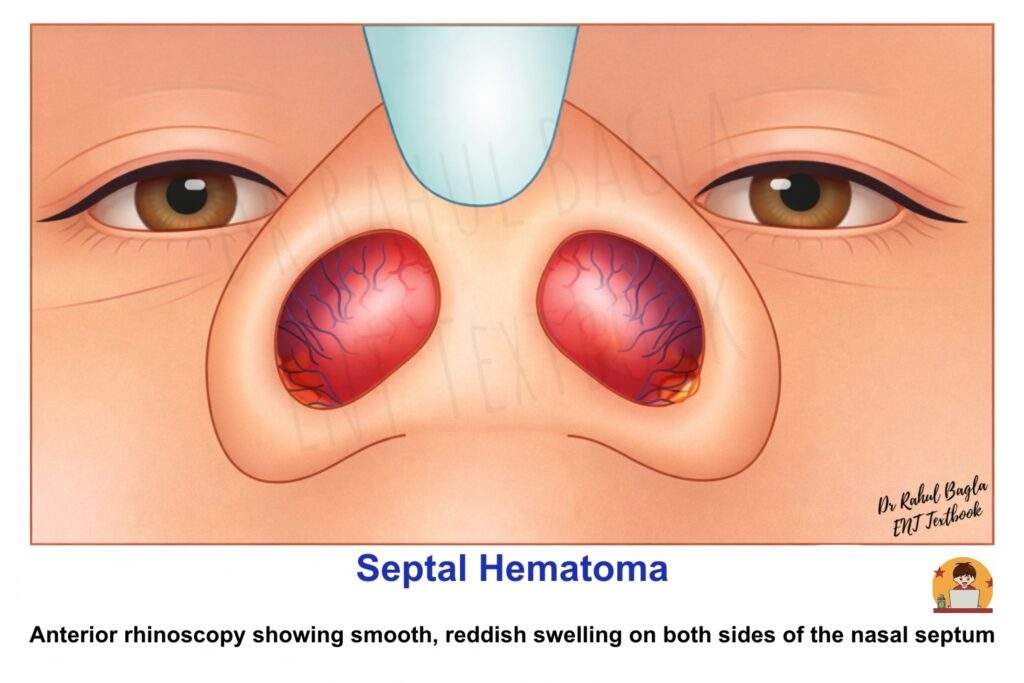
- Smooth, reddish swelling on both sides of the nasal septum
- Fluctuant swelling
- Swelling obliterates the nasal cavity
Key examination point: Septal hematoma usually presents as bilateral swelling, which helps differentiate it from a deviated nasal septum (DNS). Viva tip: “Septal hematoma appears as a bilateral soft fluctuant swelling of the septum and requires urgent drainage.”
Management.
Septal hematoma requires urgent treatment to prevent cartilage necrosis.
- Aspiration: Septal hematoma requires prompt evacuation. Needle aspiration using a wide-bore sterile needle may provide temporary decompression in selected cases, but definitive drainage is generally required.
- Incision and Drainage (Preferred): Larger haematomas are incised and drained by a small anteroposterior incision parallel to the nasal floor. Excision of a small piece of mucosa from the edge of the incision gives better drainage.
- Prevention of Recollection: After drainage, bilateral nasal packing is done, or Quilting sutures (through-and-through absorbable sutures that hold the flaps together) are applied to approximate the mucoperichondrium to cartilage.
- Antibiotics: Antibiotic therapy may be given according to the clinical situation, particularly when infection, septal abscess, contaminated trauma, or other risk factors are present.
Complications of Untreated Hematoma
If not treated early, several serious complications may occur.
- Septal abscess
- Septal cartilage necrosis
- Septal perforation
- Saddle-nose deformity
- Persistent nasal obstruction or structural nasal deformity
- Rarely, infection may extend to adjacent tissues and produce serious local (Subperiosteal abscess, Orbital cellulitis, Orbital abscess) or intracranial complications (Cavernous sinus thrombosis).
Table: Septal Hematoma vs Septal Abscess
| Feature | Septal Hematoma | Septal Abscess |
| Contents | Blood | Pus / infected collection |
| Common Setting | Usually follows nasal trauma | May develop from an infected hematoma, trauma, or surgery |
| Fever | May be absent | More suggestive and may be present |
| Pain | Common | Often prominent |
| Bilateral Swelling | Typical | May occur |
| Management | Urgent drainage | Urgent drainage + appropriate antimicrobial therapy |
| Major Danger | Septal cartilage necrosis and subsequent saddle-nose deformity | Septal cartilage necrosis, local spread, and systemic infective complications |
Septal Perforation
Definition
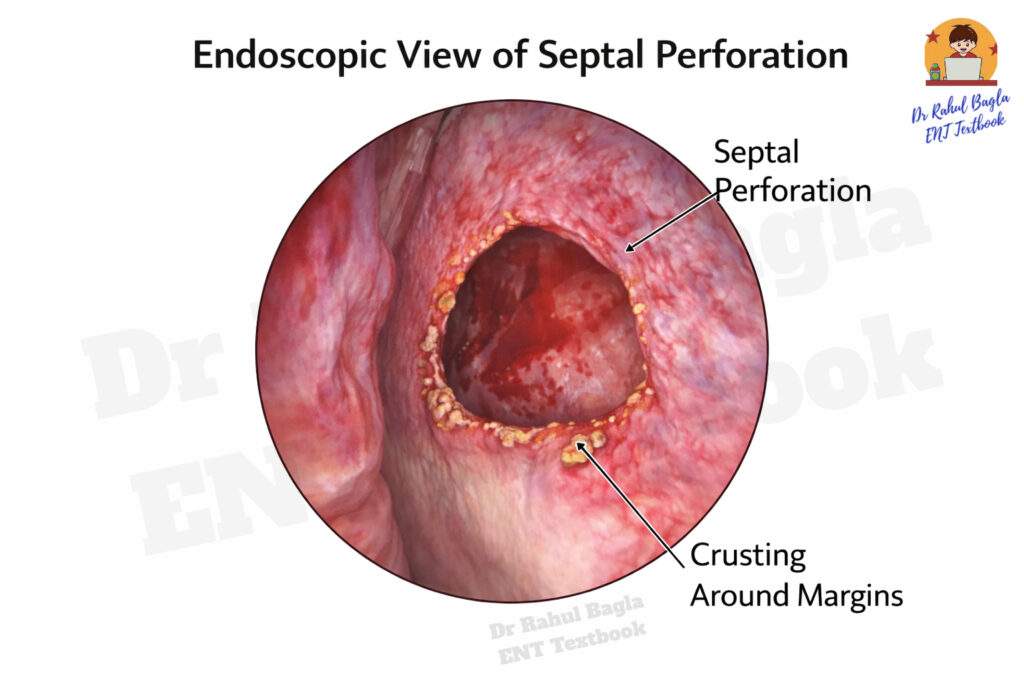
A septal perforation is a defect or hole in the nasal septum that allows communication between the two nasal cavities. The perforation usually occurs due to trauma, infection, inflammatory diseases, or iatrogenic causes. Small perforations may remain asymptomatic, whereas larger perforations often produce crusting, epistaxis, and a whistling sound during breathing.
Aetiology of Septal Perforation
- Iatrogenic: Septoplasty, SMR, nasal surgery, bilateral septal cauterisation.
- Traumatic: Nose picking, nasal trauma, foreign body and repeated instrumentation.
- Drug-related: Intranasal cocaine and other irritating substances.
- Infectious: Tuberculosis, syphilis, leprosy, rhinoscleroma and fungal infections.
- Autoimmune / Inflammatory: Granulomatosis with polyangiitis, relapsing polychondritis and sarcoidosis.
- Neoplastic: Sinonasal malignancies including squamous cell carcinoma and lymphoma.
- Chemical / Occupational: Chronic exposure to industrial irritants and caustic chemicals.
Clinical Features
The symptoms of septal perforation vary depending on the size, location, and underlying cause of the perforation. Small anterior perforations are more likely to produce an audible whistling sound, while larger perforations may produce prominent crusting, dryness, epistaxis and nasal obstruction.
Symptoms
- Crusting inside the nose (most common). Drying of nasal secretions leads to crust formation around the edges of the perforation.
- Epistaxis. Recurrent nasal bleeding occurs due to fragile mucosa and trauma during the removal of crusts.
- Whistling sound during breathing. Characteristically seen in small perforations, where air passing through the narrow defect produces a whistling noise.
- Nasal obstruction. Usually caused by crusts accumulating around the margins of the perforation.
- Recurrent bleeding after crust removal. Patients often remove crusts manually, leading to repeated trauma and bleeding.
- Dryness and nasal irritation. More common in large perforations due to excessive airflow and mucosal drying.
Clinical Examination
A detailed history and physical examination are essential to identify the cause, size, and extent of the perforation.
History. Important points include:
- History of nasal surgery (septoplasty or SMR)
- Habitual nose picking
- Use of intranasal drugs or decongestant sprays
- Occupational chemical exposure
- History of systemic diseases or infections affecting the nose
Anterior Rhinoscopy. The perforation appears as a round or oval defect in the nasal septum with surrounding crusting.
Nasal Endoscopy. Nasal endoscopy provides a better assessment of the lesion, especially when the perforation is located posteriorly. It helps to:
- Visualize posterior septal perforations
- Determine the exact size and shape
- Assess margins of the perforation
- Identify crusting, infection, or granulation tissue
Classification Based on Size. Septal perforations are commonly classified according to their diameter, which helps guide management.
- Small – Less than 0.5 cm
- Medium – 0.5 – 2 cm
- Large – Greater than 2 cm
Management
The treatment of septal perforation depends on the presence or absence of symptoms, the size of the perforation, the underlying cause, & general condition of the patient
1. Prevention. Prevention is the most important aspect of management, especially after nasal surgery. Preventive measures include:
- Using careful surgical technique during septoplasty or SMR
- Avoiding bilateral mucosal injury
- Early detection and treatment of septal hematoma or septal abscess
2. Observation. Small, asymptomatic perforations may not require active treatment. These cases can be managed with observation and periodic follow-up.
3. Conservative (Nonsurgical) Treatment. Conservative treatment is aimed at relieving symptoms, particularly crusting and bleeding.
- Saline nasal sprays. Keep the nasal mucosa moist and reduce dryness.
- Alkaline nasal douches. Help soften and remove crusts.
- Lubricating nasal ointments. Prevent mucosal dryness and irritation.
4. Septal Button. A septal button is a prosthetic device usually made of silicone material that mechanically closes the perforation. It reduces airflow through the perforation and may decrease crusting, dryness, epistaxis and whistling. It is particularly useful in patients unsuitable for surgery.
5. Surgical Treatment. Surgery is indicated in symptomatic perforations, especially when conservative treatment fails.
– Enlargement of the Perforation. Surgical enlargement of a very small septal perforation may occasionally reduce whistling caused by turbulent airflow. However, this is not a routine treatment and is considered only in selected cases.
– Surgical Repair. The aim of surgery is closure of the perforation and restoration of normal nasal physiology. Two main approaches are used:
- Closed technique. Performed through the nasal cavity, often with endoscopic assistance.
- Open technique. Performed using an external rhinoplasty approach, allowing better exposure for large perforations.
Surgical closure may use local mucosal or mucoperichondrial/mucoperiosteal flaps, with interposition grafts such as temporalis fascia, cartilage or other suitable graft materials when required.
——– End of the chapter——–
High-Yield Points for NEET PG & University Exams
Deviated Nasal Septum
- DNS: Deviation of the nasal septum from the midline.
- Common symptoms: Nasal obstruction, epistaxis, crusting and sometimes associated nasal symptoms.
- Septal spur: Sharp projection of the septum that may contribute to obstruction or epistaxis.
- C-shaped deviation: Single curvature toward one side.
- S-shaped deviation: Double curvature involving both sides at different levels.
- Caudal dislocation: Displacement of the caudal septum into one nasal cavity.
- Decongestion: Improvement suggests a reversible mucosal component; persistent obstruction suggests a structural component.
- Cottle test: Assesses the contribution of the nasal valve region.
- Mladina classification: Seven morphological types of septal deformity.
- Treatment: Treat the patient and symptoms, not the X-ray or endoscopic appearance alone.
- Septoplasty: Main contemporary surgical approach for symptomatic structural septal deviation.
- L-strut: Preserve adequate dorsal and caudal structural support.
Septal Hematoma
- Usually follows nasal trauma.
- Classic finding: bilateral smooth, reddish, fluctuant septal swelling.
- Causes acute bilateral nasal obstruction.
- ENT emergency.
- Delayed treatment can cause septal cartilage necrosis and saddle-nose deformity.
- Treatment requires urgent drainage and prevention of re-accumulation.
- Consider antimicrobial therapy according to the clinical situation.
Septal Abscess
- May develop from an infected septal hematoma or other infection/trauma.
- Suspect when septal swelling is associated with significant pain and systemic inflammatory features.
- Requires urgent drainage and appropriate antimicrobial treatment.
- Delayed treatment can destroy septal cartilage and cause deformity.
Septal Perforation
- Common causes include previous nasal surgery, trauma, digital trauma, intranasal drug use and inflammatory/infectious disease.
- Crusting and epistaxis are common symptoms.
- Small anterior perforations may cause whistling.
- Large perforations may cause dryness, crusting, bleeding and obstruction.
- Treatment depends on symptoms and cause.
- Asymptomatic perforations may require observation only.
- Symptomatic patients may benefit from humidification, saline, lubrication, a septal button or surgical repair.
- An unexplained septal perforation should prompt assessment of previous surgery or trauma, intranasal drug use, occupational exposure and systemic symptoms. Nasal endoscopy, biopsy and targeted laboratory or microbiological investigations may be required when an inflammatory, infectious or neoplastic cause is suspected.
Clinical Case Scenarios for Practical/Viva
Scenario 1: The Trauma Patient
A 25-year-old male presents to the casualty department 2 days after a fistfight. He complains of severe bilateral nasal obstruction and pain. On examination, his nose is tender, and anterior rhinoscopy reveals a smooth, reddish-blue, fluctuant swelling on both sides of the septum, completely occluding both nasal cavities.
- Q1: What is the most likely diagnosis? A: Septal hematoma.
- Q2: Why is this an emergency? A: The septal cartilage is avascular and depends on the perichondrium for nutrition. The hematoma strips the perichondrium, leading to avascular necrosis of the cartilage within 72 hours. If infected, it can lead to a septal abscess and intracranial complications.
- Q3: How will you manage this patient? A: Immediate incision and drainage under local or general anaesthesia, followed by quilting sutures or bilateral nasal packing to prevent re-accumulation, and broad-spectrum antibiotics.
Scenario 2: The Crooked Nose
A 30-year-old female presents with difficulty breathing through her nose, especially on the right side, a problem she’s had for years. She also gets frequent headaches and occasional nosebleeds from the right side. On examination, you see a sharp, shelf-like projection from the septum pressing against the right inferior turbinate. The left nasal cavity is roomy.
- Q1: What is the likely finding on anterior rhinoscopy? A: A right-sided septal spur.
- Q2: What test will you do to confirm the cause of obstruction? A: A decongestant test. If the obstruction persists after spraying a decongestant, it confirms the obstruction is primarily anatomical (the spur).
- Q3: What is the definitive management? A: Septoplasty with spur excision.
Scenario 3: The Whistling Nose
A 45-year-old man with a history of nasal surgery 10 years ago complains of a persistent whistling sound when he breathes. He also reports nasal dryness and occasional bleeding when he picks his nose.
- Q1: What is the most likely diagnosis? A: A small, anterior septal perforation.
- Q2: What is the most common cause in this patient? A: Iatrogenic from his previous nasal surgery (likely SMR).
- Q3: What is the first line of management for his symptoms? A: Conservative treatment with saline nasal sprays and lubricating ointments to reduce crusting. A silicone septal button could also be offered.
NEET PG-Style MCQs
- A 10-year-old boy presents with bilateral nasal obstruction and low-grade fever, 5 days after being hit on the nose by a cricket ball. Anterior rhinoscopy reveals a bilateral, smooth, reddish swelling of the nasal septum. Which of the following is the most appropriate next step in management? a) Prescribe a course of oral antibiotics and review in 1 week. b) Apply a nasal decongestant spray and review in 2 days. c) Perform an immediate incision and drainage. d) Order a CT scan of the paranasal sinuses.
- Which of the following is a characteristic symptom of a small, anterior septal perforation? a) Saddle nose deformity b) Bilateral nasal obstruction c) Whistling sound during breathing d) Anosmia
- The single most important step in the surgical management of a Deviated Nasal Septum (Septoplasty) is to preserve the: a) Vomer bone b) Perpendicular plate of ethmoid c) Entire quadrangular cartilage d) L-strut of cartilage
- A patient presents with recurrent epistaxis and a deviated nasal septum with a sharp projection. The most likely type of deviation is: a) C-shaped deviation b) S-shaped deviation c) Septal spur d) Caudal dislocation
- An untreated septal hematoma is most likely to lead to which of the following deformities? a) Tension pneumocephalus b) Saddle nose deformity c) Adenoid facies d) Polyps
- Cottle’s test is used to assess the patency of the: a) Osteomeatal complex b) Sphenoethmoidal recess c) Internal nasal valve d) Choana
- A 50-year-old male with a history of chronic cocaine use presents with nasal crusting and a foul smell. On examination, he has a large septal perforation. What is the most important investigation to order next? a) Fungal culture b) Biopsy from the edge of the perforation c) Serum ACE levels d) Sweat chloride test
- The primary advantage of septoplasty over submucous resection (SMR) is: a) It is a faster procedure b) It preserves adequate septal structural support and reduces the risk of nasal deformity c) It can be done under local anaesthesia d) It has a lower chance of post-operative bleeding
- Which of the following is NOT a typical causative organism in a septal abscess? a) Staphylococcus aureus b) Streptococcus pneumoniae c) Pseudomonas aeruginosa d) Haemophilus influenzae
- A patient’s nasal obstruction due to a deviated septum does NOT improve after applying a topical decongestant. This suggests that the obstruction is primarily due to: a) Allergic rhinitis b) Compensatory turbinate hypertrophy c) The nasal cycle d) A fixed anatomical deviation
Answers and Explanations
1 (c) 2 (c) 3 (d) 4 (c) 5 (b) 6 (c) 7 (b) 8 (b) 9 (c) 10 (d)
Frequently Asked Questions in Viva
- What are the major diseases of the nasal septum? Deviated nasal septum, septal hematoma, septal abscess and septal perforation.
- What is the most common symptom of a deviated nasal septum? Nasal obstruction is the most common symptom when the deviation is functionally significant.
- Why is a septal hematoma an emergency? It can compromise septal cartilage nutrition, leading to cartilage necrosis, septal abscess and saddle-nose deformity.
- What is the classic finding in a septal hematoma? A smooth, fluctuant septal swelling, usually bilateral, causing acute nasal obstruction, often after trauma.
- What causes a whistling sound from the nose? A small anterior septal perforation commonly causes nasal whistling due to turbulent airflow through the defect.
- What is the most common cause of septal perforation? Previous nasal or septal surgery is an important cause, followed by trauma, digital manipulation, intranasal drug use and inflammatory or infectious diseases.
- What does Cottle’s test assess? It assesses the nasal valve region as a potential cause of nasal obstruction.
- Is CT required for every patient with deviated nasal septum? No. DNS is primarily a clinical diagnosis. CT is useful when associated sinonasal disease, complex anatomy or surgical planning needs evaluation.
- What is the difference between septoplasty and SMR? Septoplasty corrects the septal deformity while preserving adequate structural support, whereas traditional SMR involves more extensive removal of deviated cartilage and bone.
- What is the treatment of septal perforation? Treatment depends on symptoms and cause and may include saline, humidification, lubrication, a septal button or surgical repair.
——– End——–
Reference Textbooks.
- Scott-Brown, Textbook of Otorhinolaryngology-Head and Neck Surgery.
- Cummings, Otolaryngology-Head and Neck Surgery.
- Stell and Maran’s, Textbook of Head and Neck Surgery and Oncology.
- Ballenger’s, Otorhinolaryngology Head And Neck Surgery
- Susan Standring, Gray’s Anatomy.
- Frank H. Netter, Atlas of Human Anatomy.
- B.D. Chaurasiya, Human Anatomy.
- P L Dhingra, Textbook of Diseases of Ear, Nose and Throat.
- Hazarika P, Textbook of Ear Nose Throat And Head Neck Surgery Clinical Practical.
- Mohan Bansal, Textbook of Diseases of Ear, Nose and Throat Head and Neck Surgery.
Author:

Dr. Rahul Bagla
MBBS (MAMC, Delhi) MS ENT (UCMS, Delhi)
Fellow Rhinoplasty & Facial Plastic Surgery.
Renowned Teaching Faculty
Mail: msrahulbagla@gmail.com
India
———– Follow us on social media ————
- Follow our Facebook page: https://www.facebook.com/Dr.Rahul.Bagla.UCMS
- Follow our Instagram page: https://www.instagram.com/dr.rahulbagla/
- Subscribe to our Youtube channel: https://www.youtube.com/@Drrahulbagla
- Please read. Anatomy of External Ear. https://www.entlecture.com/anatomy-of-ear/
- Please read. Anatomy of Temporal Bone. https://www.entlecture.com/anatomy-of-temporal-bone/
- Please read. Stenger’s, Chimani Moos, Teal test. https://www.entlecture.com/special-tuning-fork-tests/
Keywords: Deviated Nasal Septum Notes For MBBS Students, DNS Causes Symptoms And Management, Septal Hematoma Management, Septal Perforation Causes And Treatment, Nasal Septum Diseases CBME, NEET PG DNS Questions, Septoplasty Vs SMR, Cottle Test Clinical Significance, Mladina Classification DNS, Septal Spur Symptoms, Septal Abscess Complications, Saddle Nose Deformity Causes, DNS Clinical Features, Septal Perforation Treatment, ENT Nasal Septum MCQs, Nasal Septum Viva Questions, High-Yield ENT Revision Notes, Nasal Obstruction Differential Diagnosis, CBME ENT Notes, ENT Practical Exam Questions,
very nice, loved it fullly